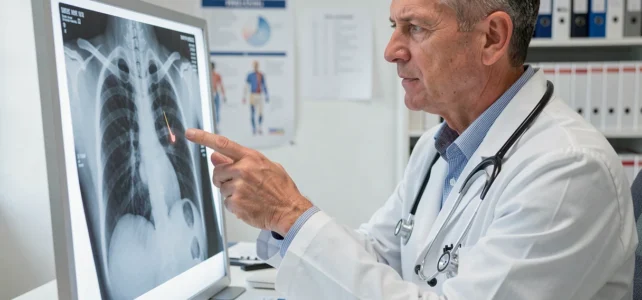
The azygos fissure is an anatomical variant of the right lung, most often identified incidentally during a thoracic imaging examination. It results from an unusual path of the azygos vein during fetal development and is not, in itself, a pathology. Its accidental discovery raises legitimate questions about its consequences, any associated symptoms, and how to approach concurrent chest pain.
Embryological mechanism of the azygos fissure and azygos lobe
During fetal life, the azygos vein normally descends along the mediastinum to join the superior vena cava. When its path goes above the right upper lobe instead of around it, it carries the parietal pleura with it. This movement creates a fold formed by four pleural layers, which progressively digs into the lung parenchyma.
This fold constitutes the false azygos fissure. The term is precise: it is not a normal anatomical fissure separating two functionally distinct lobes. The portion of parenchyma isolated between the mediastinum and this pleural mesentery is called the azygos lobe, but it does not have an autonomous bronchovascular pedicle. It usually belongs to the apical segment of the right upper lobe.
To obtain information on azygos fissure pain, it is necessary to distinguish this anatomical feature from true pulmonary anomalies that can generate specific symptoms.
Incidental finding on chest CT: why the frequency is increasing
The azygos fissure is now predominantly identified as an incidentaloma, meaning a finding not sought during an examination performed for another reason. The increasing deployment of low-dose CT screening, particularly in the context of lung cancer follow-up, has mechanically increased the number of these incidental discoveries.
On a frontal chest X-ray, the fissure appears as a thin vertical opaque band extending from the apex of the lung, parallel to the right edge of the mediastinum but clearly outside of it. Computed tomography identifies it even more easily and allows confirmation of the aberrant path of the azygos vein.
What imaging shows and what it does not show
The typical and isolated appearance of an azygos fissure does not warrant specific follow-up. Current recommendations, particularly those from the Fleischner Society, classify perifissural nodules less than 10 mm with well-defined edges, oval, lentiform, or triangular in shape, as presumed benign. This classification directly applies when a nodule is adjacent to an azygos fissure and presents this radiological profile.
The difficulty arises when the nodule does not meet these criteria or when the fissure coexists with other anomalies. In these cases, follow-up imaging or specialized consultation becomes relevant.
Azygos fissure and symptoms: what is part of the variant and what is not
The question often arises: can an azygos fissure cause chest pain? The available data do not allow for a direct attribution of painful symptoms to this anatomical variant. The azygos fissure itself is asymptomatic in the vast majority of documented cases.
When chest pain is observed in a patient with an azygos fissure, several avenues must be explored before considering a causal link:
- A pathology of the azygos vein itself, such as abnormal dilation or, more rarely, thrombosis of the azygos venous system, which can cause back or chest pain
- An intercurrent pulmonary condition (infection, effusion, suspicious nodule) unrelated to the fissure but revealed by the same examination
- Musculoskeletal or pleural pain whose location coincides with the location of the fissure on imaging, creating a false impression of correlation
The main risk is to focus attention on the fissure and neglect a distinct cause of the pain. The differential diagnosis remains the priority in the face of any chest pain associated with this finding.
Azygos vein and caval venous system: when the anatomical variant complicates treatment
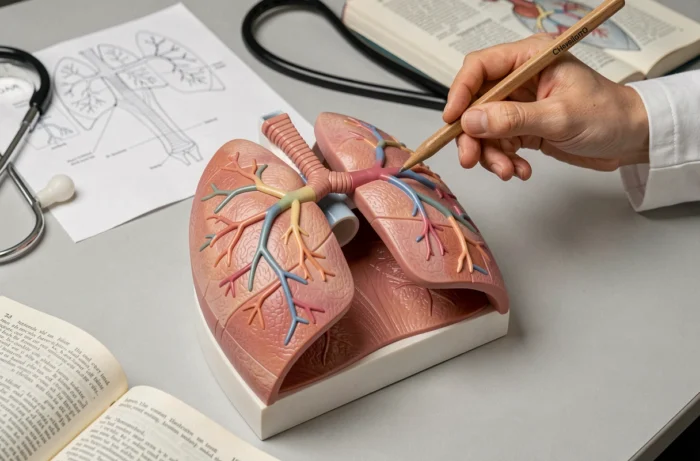
The azygos vein plays a role as a collateral pathway between the superior and inferior caval venous systems. It drains blood from the walls of the thorax and abdomen. In the event of obstruction of the superior vena cava, the azygos system can partially compensate for venous return.
An azygos fissure implies a modified path of this vein, which can have practical consequences in certain clinical situations:
- Placement of central catheters or intravenous devices: the aberrant path must be identified to avoid inappropriate positioning
- Thoracic surgery: preoperative knowledge of the variant alters the surgical approach, particularly during lobar or segmental resections of the right lung
- Interpretation of mediastinal widening on imaging: the atypical position of the azygos vein can mimic a mass or lymphadenopathy if the radiologist does not identify the variant
These situations remain infrequent but justify that the azygos fissure be systematically mentioned in the radiological report, even when it is considered benign.
Management of chest pain in a patient with an azygos fissure
The treatment of chest pain in a patient in whom an azygos fissure has been identified does not fundamentally differ from standard management. The primary goal is to rule out cardiovascular and pulmonary emergencies before addressing the anatomical anomaly.
Diagnostic approach and appropriate treatments
The initial assessment generally includes a clinical examination, an electrocardiogram, and chest imaging. If the pain is of pleural or musculoskeletal origin, treatments are based on anti-inflammatories and standard analgesics. In the case of venous thrombosis of the azygos system, anticoagulant treatment may be indicated, with follow-up tailored to the patient’s risk level.
No specific treatment targets the azygos fissure as such. It requires neither medication, nor surgery, nor special monitoring when it is isolated and appears typical. Field reports sometimes differ on the appropriateness of distant follow-up, but current recommendations do not advocate for it in the absence of associated anomalies.
The azygos fissure remains an anatomical variant whose knowledge primarily benefits healthcare professionals who interpret imaging examinations or plan an invasive procedure. For the patient, the main takeaway is that this feature does not impair lung function or life expectancy, and that any chest pain deserves a thorough evaluation regardless of its presence.